To come off GLP-1 medication, step the dose down with the prescribing doctor rather than stopping overnight, never on your own. After the STEP 1 extension's overnight stop, about two-thirds of the lost weight returned within a year (Wilding 2022), and in SURMOUNT-4 weight rose 14.0% on average in the 52 weeks after a switch to placebo (Aronne 2024); individual results vary. The GetLean GLP-1 Taper Plan plans your taper from the first consultation with Dr Quek, toward your lowest effective dose and, where clinically appropriate, off the medication.
In SURMOUNT-MAINTAIN, adults who stepped down to a lower dose of tirzepatide after 60 weeks were still 16.6% below their starting weight a year later (Horn 2026); individual results vary. At GetLean the programme is designed to end, through the GetLean GLP-1 Taper Plan: the habits are built while the medication is working, Dr Quek steps the dose down at the monthly reviews towards the lowest effective dose, and support can carry on after the taper.
GetLean GLP-1 Taper Plan: GetLean's plan for coming off GLP-1 medication, set from the first consultation, in three stages (GLP-1 as a catalyst, build the habits, track and taper), with the dose stepped down at Dr Quek's monthly reviews towards your lowest effective dose and, where clinically appropriate, off the medication.
Stopping is the part of GLP-1 treatment with the least planning around it. Every trial that measured regain took the medication away, by stopping it or by switching people to placebo. In the STEP 1 extension the lifestyle support ended on the same day, and about two-thirds of the lost weight returned within a year (Wilding 2022). That is the scenario a planned exit is designed to avoid. This guide covers how a planned exit works: habits built while the medication is working, the dose stepped down at monthly reviews, and support that carries on after the taper; then what the withdrawal trials measured, and why the weight returns after an overnight stop.
Randomised withdrawal trial: a study in which everyone is treated first, then randomly assigned either to continue or to switch to a placebo. It measures the effect of taking the medication away against the effect of carrying on.
How do I get off GLP-1?
Where clinically appropriate, with a plan and with the doctor who prescribed it. A planned exit has three stages: GLP-1 as a catalyst, while the medication keeps appetite quiet; build the habits that hold the result while it is still working; and track and taper, with the dose stepped down rather than stopped overnight and support carrying on after the taper. Never stop or change a prescribed medicine on your own; that is a conversation with the doctor who prescribed it. At GetLean the programme is designed to end, and the taper is planned from the first consultation and set at Dr Quek's monthly reviews as the response comes in, towards the lowest effective dose and, where clinically appropriate, off the medication entirely. While the medication is keeping appetite quiet, the daily WhatsApp coaching builds the eating pattern and the training habit, with the aim that both are routine by the time the dose comes down. Every dose change is his decision, taken on how the person has responded and what they can tolerate.
What the withdrawal trials measured
Every one of them took the medication away, by stopping it or by switching people to placebo.
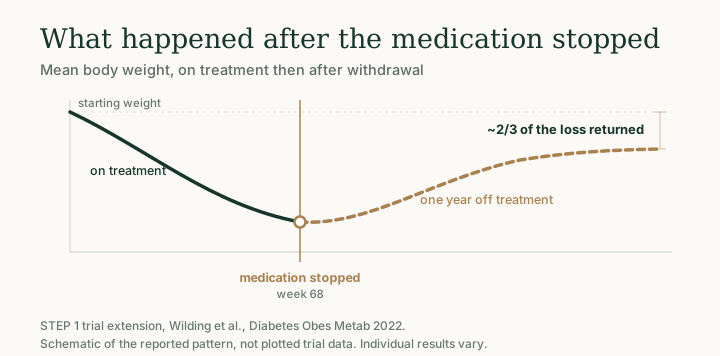
In the STEP 1 extension, 327 adults who had lost 17.3% of body weight over 68 weeks on semaglutide stopped both the medication and the trial's lifestyle intervention at week 68, and were followed for a year. They regained 11.6 percentage points of that loss, about two-thirds of it, and finished 5.6% below their original weight (Wilding 2022). STEP 4 with semaglutide and SURMOUNT-4 with tirzepatide were randomised withdrawal trials: after a run-in on the medicine, people were randomised to continue it or to switch to placebo (Rubino 2021, Aronne 2024).
Three things get dropped when the two-thirds figure is retold, and each of them changes what it means. It is a group average with a standard deviation of 7.7 percentage points around it. The regain decelerates rather than running at a constant rate. And the trial groups ended lighter than they began — in SURMOUNT-4 the placebo-switched group was still 9.9% below baseline at week 88. Why two-thirds of the weight comes back works through each of those in full.
A 2026 systematic review pooled six randomised trials of stopping GLP-1 receptor agonists, covering 3,236 people, and estimated that 60% of the weight lost on treatment was regained one year after stopping, with the regain slowing over time; beyond 52 weeks its model was extrapolated, levelling off at an estimated 75.3% of the weight lost, which is below the pre-treatment weight (Budini 2026). Individual results vary.
In SURMOUNT-4, the group switched to placebo saw its weight rise by 14.0% on average from week 36 to week 88 (Aronne 2024). That is a rise on the weight at week 36, while the STEP 1 extension's two-thirds is a share of the weight lost, so the two figures are measured differently and cannot be set directly side by side.
In Singapore tirzepatide's current registrations carry both a type 2 diabetes and a weight-management indication, while the 2023 injection registration SIN16718P carries type 2 diabetes only (Singapore NDF). Every tirzepatide figure above is reported as a trial result rather than as an outcome to expect.
What the withdrawal trials did not measure
Two absences matter more than anything the trials found, because both are routinely filled in with confident claims.
Appetite was never measured. The STEP 1 extension, STEP 4 and SURMOUNT-4 recorded body weight and cardiometabolic markers. None of them recorded hunger, craving or food intake after stopping. "Appetite comes back when you stop" is a reasonable inference from the medicine clearing the system — semaglutide has an elimination half-life of about a week and is present in the circulation for roughly five to seven weeks after a last 2.4 mg dose (product information), tirzepatide's is about five to six days (product information) — but a half-life describes drug concentration, not how long a downstream effect lasts. Nobody has measured the time course of appetite return. Appetite after stopping separates what was inferred from what was observed.
The composition of the regained weight was never measured either. The largest meta-analysis of withdrawal trials pooled body weight, waist circumference and BMI, and contains no fat-mass or lean-mass data at all (Berg 2025). "It comes back as fat" is an extrapolation from a different literature — severe semi-starvation refeeding — and it has not been demonstrated after GLP-1 treatment. What regained weight is actually made of sets out why the extrapolation is plausible and why plausible is not the same as measured.
The case for protecting muscle does not need that claim, and it is weaker for borrowing it. It rests on the composition of the weight lost, which is well evidenced: in the SURMOUNT-1 body-composition sub-study, roughly 75% of the weight lost was fat and about 25% lean mass — the same ratio in the tirzepatide arm and the placebo arm (Look 2025).
What happens when you stop GLP-1?
The effect on appetite wears off as the medicine clears, and in the STEP 1 extension, where the medication and the lifestyle support stopped on the same day, with no taper, about two-thirds of the lost weight returned within a year, with the group still 5.6% below its starting weight (Wilding 2022). That is a group average with wide individual spread, and clinical-trial figures describe the populations studied; individual results vary.
The medication quiets appetite while it is being taken. Stop it overnight and that effect fades over the following weeks as the medicine clears; the habits in place by then are what is left. That is biology, not a lack of willpower, and it is why an overnight stop is the scenario a planned exit is designed to avoid. Rebound is the pressure the habits and the taper are there for. Never stop or change a prescribed medicine on your own; that is a conversation with the doctor who prescribed it.
The maintenance phase covers what actually changes on the day the prescription ends, which is narrower than most people assume: the appetite effect stops, and everything built around it carries on.
Can I just stop GLP-1?
Not on your own: stopping or changing a prescribed medicine is a decision for the doctor who prescribed it, so raise it with them first. Every trial that measured regain took the medication away, by stopping it or by switching people to placebo, and that is the scenario a planned exit is designed to avoid. In the STEP 1 extension, where the medication and the lifestyle support stopped on the same day, about two-thirds of the lost weight returned within a year (Wilding 2022); that is a group average with wide individual spread, and individual results vary. At GetLean the alternative is a step-down rather than a stop: Dr Quek brings the dose down at the monthly reviews, towards the lowest effective dose and, where clinically appropriate, off the medication entirely. A patient can raise a change at any check-in, and any change is his decision. Side effects are a separate question: the side-effects guide covers what is common on GLP-1 medication, what is uncommon but serious, and when to stop and call a doctor.
How do I wean off GLP-1?
Gradually, with the prescribing doctor, and where clinically appropriate: the dose is stepped down rather than stopped overnight, never changed on your own. The withdrawal trials took the medication away, by stopping it or by switching people to placebo, and in the STEP 1 extension, which stopped it overnight, about two-thirds of the lost weight returned within a year (Wilding 2022). At GetLean we favour a gradual reduction under a doctor's guidance rather than a cliff-edge stop, which allows appetite to adjust incrementally while the habits built during treatment take over. Dr Quek steps the dose down at the monthly reviews, towards the lowest effective dose. Doctors sometimes call this step-down a taper, or reverse titration.
Stepping down is a different picture from stopping. In SURMOUNT-MAINTAIN, adults who stepped down to a lower dose of tirzepatide after 60 weeks were still 16.6% below their starting weight a year later (Horn 2026). Weaning off GLP-1 covers how a planned taper works. If you are already on Mounjaro with another doctor, you can move to GetLean and plan the taper with Dr Quek: how to switch, step by step.
How the medication ended in three trials this guide cites, and where each group stood afterwards; these are group averages, and individual results vary.
| Trial | Medicine | How the medication ended | Where the group stood afterwards | Source |
|---|---|---|---|---|
| STEP 1 extension | semaglutide | Stopped overnight at week 68, with no taper, together with the trial's lifestyle intervention | Over the following year, regained 11.6 percentage points of a 17.3% loss, about two-thirds of it; finished 5.6% below original weight | Wilding 2022 |
| SURMOUNT-4 | tirzepatide | Switched to placebo after a 36-week lead-in | Placebo-switched group still 9.9% below baseline at week 88 | Aronne 2024 |
| SURMOUNT-MAINTAIN | tirzepatide | Stepped down to a lower dose after 60 weeks | Still 16.6% below starting weight a year later | Horn 2026 |
What does the lowest effective dose mean?
The principle a prescriber works to is the lowest effective dose: the smallest dose that still achieves the clinical goal, rather than the highest dose a person can tolerate. It is general prescribing practice rather than a trial finding, and it is a principle rather than a number, because the dose that fits one patient will not fit another. Dose changes depend on how someone has responded, what side effects they have had, what else they take and what the goal is.
At GetLean, dose changes are made at the monthly check-in with Dr Quek. A patient can raise a change at any check-in, and any change is his decision, taken on how the person has responded and what they can tolerate.
How long should someone stay on it?
Long enough to reach the goal at a planned pace and build the habits that hold it, then a planned taper. No rule fixes a number of months; at GetLean the length is set at Dr Quek's monthly reviews.
Three figures get quoted on this question, and each is easy to misread: the longest exposure data in the field, the shape of the weight-loss curve, and a two-year limit from England.
The longest continuous exposure published is about four years, from a trial that was not a weight-loss trial: weight loss continued to about week 65 and was then sustained to a mean −10.2% at week 208 against −1.5% on placebo (Ryan 2024). Everyone enrolled was aged 45 or over with established cardiovascular disease, and diabetes was an exclusion (Lincoff 2023), so that figure describes a secondary-prevention population rather than a weight-management one.
A plateau is the point to plan the taper with the doctor, not a signal to stop on one's own. In a two-year trial in adults with obesity and without diabetes, weight loss plateaued at around week 60 (Garvey 2022). In a formal time-to-plateau analysis for tirzepatide, median times ran from about 24 to 36 weeks by starting BMI class and roughly nine in ten responders had plateaued by week 72 — an analysis restricted to adherent participants who reached at least 5% loss, and authored largely by the manufacturer (Horn 2025). At GetLean, reaching a plateau is a conversation for the monthly review with Dr Quek, where the taper is set as the response comes in.
The two-year figure people quote is a funding decision. England's NHS guidance recommends semaglutide for weight management only if it is used for a maximum of two years within a specialist service (NICE 2023). That is a health-technology assessment reflecting cost-effectiveness modelling, not a safety or efficacy finding, and it has no standing in Singapore. How long should you stay on GLP-1 traces each of these numbers to its source, and sets out how the length of treatment is set.
How is the exit from GLP-1 planned from day one?
In three stages, set from the first consultation: GLP-1 as a catalyst, while appetite is quiet; build the habits, at a planned pace; and track and taper, with the dose stepped down at the monthly reviews rather than stopped overnight and support carrying on after the taper. The things that hold a result take months to build, and the months when appetite is quiet are the easiest time to build them. At GetLean, the programme is designed to end: our philosophy is that GLP-1 medication should act as a catalyst — not something to depend on indefinitely.
- GLP-1 as a catalyst: use the quiet window. The medication keeps appetite quiet, and those months are the easiest time to build what holds the result.
- Build the habits, at a planned pace. While the medication is keeping appetite quiet, the daily WhatsApp coaching builds the eating pattern and the training habit, at a planned pace so the habits have months to set, with the aim that both are routine by the time the dose comes down.
- Track and taper, then stay after the taper. Dr Quek brings the dose down at the monthly reviews, towards the lowest effective dose, rather than stopping it overnight, as the STEP 1 extension did. Coaching and reviews can continue after the taper, and if the weight starts coming back, a review with Dr Quek is the way back in.
The timing matters because a loss becomes more durable the longer it is held: once it has been kept for two to five years, the chance of longer-term success rises substantially (Wing and Hill 2001). A plan that starts when the prescription ends begins that slow process just as the appetite effect is fading. A plan that starts on day one gives the habits months of practice before the dose comes down.
At GetLean the taper is planned from the first consultation and set at the monthly reviews as the response comes in, rather than written as a fixed schedule on day one. The intention to end is fixed at the start; the pace follows what has actually happened.
Does exercise help keep weight off after stopping GLP-1?
In a Copenhagen randomised trial that followed adults for a year after treatment ended, those who had combined a GLP-1 medication with supervised exercise were more likely than those who had taken the medication alone to still hold a loss of at least 10% of their starting weight (Jensen 2024). The medication was liraglutide, an earlier GLP-1 medicine, and the initial loss came from a low-calorie diet. Resistance training keeps lean mass through a deficit: lean mass was statistically unchanged in the trials where resistance training accompanied caloric restriction (Lopez 2022). Muscle that is still there when the medication stops carries on doing its job. Individual results vary.
How do you keep the weight off after stopping GLP-1?
With habits, built while the medication is working rather than after it stops. The habits that hold a loss are well described: the National Weight Control Registry recorded 784 people who had kept at least 13.6 kg off for five years on average, reporting a low-fat diet and around an hour a day of physical activity (Klem 1997). Followed for a year, 59% of registry members held their loss, and having already held it for two years or more was associated with a lower chance of regaining (McGuire 1999). Members who cut back on weighing themselves regained 4.0 kg over a year against 1.1 kg in those who weighed themselves more often (Butryn 2007). Registry data is observational, a record of what people who kept weight off report doing, and those are the habits the daily WhatsApp coaching builds. Individual results vary. The habits that predict keeping weight off reads that literature in full, and planning your exit from day one sets out what a taper-oriented programme is made of.
What happens after the taper at GetLean?
Finishing the taper does not have to end the support. After the taper, a patient can keep the daily WhatsApp coaching and the monthly reviews with Dr Quek by continuing the monthly subscription, if they wish. If the weight starts coming back, they can come back to Dr Quek at any time: a restart begins with a review consultation, and whether to restart the medication is his decision at that review.
Designed to end: a programme whose pace and taper off the medication are planned from the first consult, so the result holds after the medication stops.
The medicines by name: do you have to take Mounjaro or Wegovy forever?, coming off Mounjaro, coming off Wegovy, withdrawal symptoms: what is real, is a lower maintenance dose enough? and stopping before surgery or a scope.
Stopping, regaining, restarting
Stopping and restarting is the normal pattern in practice rather than the exception. Among 125,474 US adults, 64.8% of those without type 2 diabetes had stopped within a year, and about 36% of those who stopped had restarted within the following year, with weight regain after stopping strongly associated with restarting (Rodriguez 2025). That is observational data from a US insurance and access context that does not transfer to Singapore.
How well a second course works has not been published. Reinitiation is well counted; the weight outcome of a restart after stopping and regaining is not reported in any human study. A direct experiment has been run in animals: in male mice with diet-induced obesity, restarting semaglutide did produce weight loss, but the cycled animals "failed to reach the prior weight nadir achieved during cycle 1", and the authors state that validation in females and in human populations is essential before drawing any translational conclusion (Son 2026). A second course has not been shown to work less well in people, and it has not been shown to work as well either.
Whether the cycling itself does harm is contested, and the literature changed direction recently. A meta-analysis of 23 cohort studies covering 441,199 people associated body-weight fluctuation with roughly 35–50% higher relative risks of all-cause mortality, cardiovascular mortality, cardiovascular disease and hypertension (Zou 2019). A 2026 Lancet Diabetes & Endocrinology Personal view reappraised the same body of work and concluded that current evidence does not support a causal link between weight cycling itself and clinical harm in people with obesity, attributing the associations to ageing, unintentional weight loss and reverse causality (Magkos 2026). Those are observational cohorts against an argued appraisal by two authors. Both are citable; neither settles it. Restarting after a rebound works through what is counted, what is contested and what is unknown.
A former GetLean patient who wants to restart has a review consultation with Dr Quek first. The previous dose can usually be continued where it is clinically appropriate; that is his decision at the review, not an automatic resumption.
Micro-dosing and dose-stretching
This comes up constantly as a gentler alternative to stopping, and it has no evidence base in either direction.
As of 14 October 2026 the indexed literature on micro-dosing is letters, commentaries, a brief report, a narrative review and one records study, and no trial has reported; one peer-reviewed characterisation calls the practice subtherapeutic and unsupervised, driven by cost and tolerability (microdosing literature; Beck 2026; Murugadoss 2026). There is no published trial, no pharmacokinetic study, no regulator position and no obesity professional body statement. That absence cuts both ways: nobody has shown it works, and nobody has shown it does not.
The product information does not sanction it. Both medicines' labels set a minimum interval between two doses, permitting the weekly injection day to be moved, and the only upper bound anywhere is the missed-dose rule — which instructs skipping the dose rather than adopting a longer interval (product information). The FDA warning most often cited in this discussion runs the other way as well: its concern is compounded semaglutide and tirzepatide used at doses beyond the approved label — more product in a single dose, doses taken more frequently, or titration increased more quickly — not smaller ones (FDA). It is a US statement about compounded product, not about the licensed pens a Singapore prescription is filled with.
That is the label. Under the GetLean GLP-1 Taper Plan, set with Dr Quek, microdosing means taking the medicine below its labelled dose or schedule: GLP-1 microdosing at GetLean, step by step.
In a cohort of 7,881 US adults, 80.8% were on a low maintenance dose (below semaglutide 1.7 mg or tirzepatide 10 mg), and the cohort's average one-year weight loss was 8.7%, against 13.7% and 18.0% among those who stayed on treatment at a high maintenance dose (Gasoyan 2025). It is observational, its "low" category means ordinary titration doses rather than the sub-therapeutic fractions people mean by micro-dosing, and people on lower doses may be there because of side effects, cost or a clinician's judgement — what is common on GLP-1 medication, what is uncommon but serious, and when to stop and call a doctor covers the first of those. Micro-dosing and dose-stretching sets out the labels, the searches and what stays unknown. Any change to a prescribed dose is a decision for the prescribing doctor.
What does microdosing mean at GetLean?
At GetLean, microdosing means taking the medicine below its labelled dose or schedule, set with Dr Quek as part of the GetLean GLP-1 Taper Plan for coming off. When you have reached your goal weight and want to come off your GLP-1 medicine, stopping all at once is usually the hardest way to do it. The GetLean GLP-1 Taper Plan brings your appetite back gradually instead, and it gets you below the labelled dose or schedule in two ways, and often uses both.
Lower doses. GLP-1 medicines are started at a low dose and stepped up to an effective one. Tapering runs the same steps in reverse. You come down to the dose you were on before and stay there until your hunger and cravings are at a level you can handle: someone who reached their goal on Mounjaro 15 mg might come down to 10 mg and stay on 10 mg until they are ready.
Longer gaps between injections. Instead of one injection every 7 days, you might inject every 8, 9 or 10 days. The two can be combined: for example, going from Mounjaro 15 mg once a week to 10 mg every 10 days.
One safety rule. On higher doses (7.5, 10 or 15 mg), if you go more than 10 days without an injection, the taper restarts on a lower dose. Taking a high dose after a long break can cause stomach and gut side effects, including pancreatitis. Speak to us before your next dose.
Every GetLean GLP-1 Taper Plan is set with Dr Quek, around your habits, your lifestyle and how confident you feel at each step. GLP-1 microdosing at GetLean, step by step sets out the whole plan. Book a consultation to plan yours.
What this adds up to
The regain evidence describes one scenario: the medication taken away, by stopping it or by switching people to placebo, and in the STEP 1 extension, which stopped it overnight with no taper, the lifestyle support ended the same day. A planned exit is built around the opposite. The habits are built while the medication is working, with daily WhatsApp coaching; the dose is stepped down at Dr Quek's monthly reviews rather than stopped; and the support can carry on after the taper.
The parts under a patient's control deserve the attention: the muscle protected while the medication is doing its work (the subject of protecting muscle on GLP-1), the eating pattern that stops requiring effort, the training that becomes ordinary. Those are the things that do not stop when a prescription does.
Clinical-trial figures describe the populations that were studied; individual results vary and are not guaranteed. Never change or stop a prescribed medicine on your own — that is a conversation with the doctor who prescribed it. If you are considering treatment, book your consult and speak to a doctor about whether it is suitable for you.
Read the transcript
“When can I stop taking GLP-1 medication?”
That’s a question I hear often from my patients at GetLean.
And it’s a very fair question. In fact, I think everyone should ask it before starting treatment.
For some people, coming off may be appropriate. Others may need ongoing treatment. The answer depends on the individual.
But the conversation should start early. Because there’s useful work we can do while you’re on treatment to prepare for what comes next.
Let me explain.
Medication can help quiet your appetite. But I also want you to understand your body, your food, and the habits you’re building.
A useful place to start is understanding how much energy your body needs.
You may have heard the term “basal metabolic rate”, or BMR. That’s the energy your body needs at rest to keep basic functions going, like breathing and circulation.
Then there’s the additional energy you use throughout the day—walking, working, exercising, and digesting food.
Together, these make up your total daily energy needs.
That total—not your BMR alone—is the starting point for estimating how much you might eat to lose weight, or to maintain it once you reach a weight that’s appropriate for you.
It’s an estimate we adjust based on what actually happens over time.
The next part is getting familiar with what’s in the food you eat.
Take two eggs.
Two boiled eggs contain roughly 150 calories. Scramble those same eggs without adding anything, and the calories are broadly similar.
But add a tablespoon of butter, and that adds about another 100 calories—before any cheese, toast or sauce.
The difference is what goes into the pan.
Or think about the sausage bun you pick up from the bakery.
It looks small. You might barely register it as a meal. But there’s the bread, the sausage, and sometimes mayonnaise or other toppings. The portion and recipe matter much more than how small it looks.
Drinks count, too.
A small, 330-millilitre regular beer can contain around 140 calories, depending on the brand and strength.
To give you a sense of scale, that can be comparable to the additional energy used during roughly half an hour to 40 minutes of walking at a purposeful pace. The amount varies with your body size and how fast you walk. It’s an illustration, not an exact calculation for you.
These are the everyday details I want you to become comfortable with.
Knowing your usual portions. Looking at how food is prepared. Remembering the cooking oil, sauces and drinks.
And building balanced meals with vegetables, protein and fibre-rich foods that you actually enjoy eating.
You can still enjoy meals with your family and go out with friends. The goal is to make informed choices that fit your life.
At GetLean, daily WhatsApp coaching helps you put those habits into practice while you’re on the programme.
Now, those habits matter—but they don’t guarantee that someone can stop medication without regaining weight.
You may have heard about the STEP 1 extension study. Participants who had received a GLP-1 medication regained, on average, about two-thirds of their lost weight within a year of stopping.
Both the medication and the study’s lifestyle support had ended. The study didn’t test whether gradually reducing the dose would change that result.
So it isn’t a prediction for you, or proof of what tapering can achieve. It’s a reason to take the longer-term plan seriously.
At our monthly reviews, we look at how you’re doing and whether your treatment should change.
Where appropriate, we work towards the lowest effective dose and consider whether you can come off medication entirely.
There’s no single stopping schedule for everyone. Every dose change needs to be a doctor’s decision.
Medication can have side effects and isn’t suitable for everyone. Please don’t stop or change a prescribed medicine on your own.
So when you ask me, “When can I stop?”, I want us to talk about more than a date.
Let’s talk about your treatment, your everyday habits, and the support you’ll need next.
That’s the plan we should be building from day one.
Common questions
How much weight comes back after stopping GLP-1 medication?
In the STEP 1 extension, where the medication and the lifestyle support stopped on the same day, with no taper, about two-thirds of the lost weight returned within a year, and the group was still 5.6% below its starting weight (Wilding 2022). That is a group average with wide individual spread, and clinical-trial figures describe the populations studied. A planned exit is built around that result: the habits are built while the medication is working, and the dose is stepped down rather than stopped.
How does GetLean bring the dose down?
Gradually, at Dr Quek's monthly reviews, rather than stopping it overnight, as the STEP 1 extension did. The taper is planned from the first consultation and set as the response comes in, so the schedule is set for each patient. The aim is the lowest effective dose, and every dose change is his decision.
How long should you stay on GLP-1 medication?
Long enough to reach the goal at a planned pace and build the habits that hold it, then a planned taper. No rule fixes a number of months; at GetLean the length is set at Dr Quek's monthly reviews. A plateau is the point to plan the taper with the doctor, not a signal to stop on one's own.
Does the weight come back as fat?
Nobody has measured it. No GLP-1 withdrawal trial or meta-analysis reports the fat-versus-lean split of the weight that returns — the largest pooled analysis recorded body weight, waist circumference and BMI only (Berg 2025). What is well measured is the composition of the weight lost, which is where muscle protection earns its place.
Is it bad to stop and start again?
The evidence disagrees with itself. A meta-analysis of 23 cohorts covering 441,199 people associated body-weight fluctuation with a 35–50% higher relative risk of death and cardiovascular disease (Zou 2019); a 2026 Lancet Diabetes & Endocrinology Personal view reappraised that literature and concluded it does not support a causal link (Magkos 2026). Restarting is common — about a third of US adults who stopped had restarted within a year (Rodriguez 2025) — and no human study has published how well a second course works.
Does micro-dosing let you come off more gently?
There is no trial evidence either way yet. As of 14 October 2026 the indexed literature on micro-dosing is letters, commentaries, a brief report, a narrative review and one records study, and no trial has reported; no regulator or obesity professional body has published a position on it (microdosing literature; Beck 2026; Murugadoss 2026). The product information sets a minimum interval between doses and never a maximum (product information). That is the label. Under the GetLean GLP-1 Taper Plan, set with Dr Quek, microdosing means taking the medicine below its labelled dose or schedule, and the plan brings your appetite back gradually instead of stopping all at once (GLP-1 microdosing at GetLean, step by step).
What does microdosing mean at GetLean?
At GetLean, microdosing means taking the medicine below its labelled dose or schedule, set with Dr Quek as part of the GetLean GLP-1 Taper Plan. The GetLean GLP-1 Taper Plan gets you there in two ways, and often uses both: lower doses, where you come down to the dose you were on before and stay there until your hunger and cravings are at a level you can handle; and longer gaps between injections, where instead of one injection every 7 days, you might inject every 8, 9 or 10 days. The two can be combined: for example, going from Mounjaro 15 mg once a week to 10 mg every 10 days. On higher doses (7.5, 10 or 15 mg), if you go more than 10 days without an injection, the taper restarts on a lower dose. Taking a high dose after a long break can cause stomach and gut side effects, including pancreatitis. Speak to us before your next dose.
Is weight regain after stopping a willpower problem?
No. The appetite suppression is pharmacological, and the medicine clears over weeks after a last dose (product information). Stopped overnight, the appetite effect fades over the following weeks, and the habits in place by then are what is left. That is biology, not a lack of willpower, and it is why the habits are built while the medication is still working.
What happens after the taper at GetLean?
A patient can keep the daily WhatsApp coaching and the monthly reviews with Dr Quek by continuing the monthly subscription, if they wish. If the weight starts coming back, they can come back to Dr Quek at any time; a restart begins with a review consultation, and whether to restart the medication is his decision.
How to stop GLP-1?
With the doctor who prescribed it, and gradually: the dose is stepped down rather than stopped overnight, and never changed on your own. At GetLean that is the GetLean GLP-1 Taper Plan: Dr Quek steps the dose down at the monthly reviews towards your lowest effective dose and, where clinically appropriate, off the medication, while daily WhatsApp coaching keeps the eating and training habits in place. Individual results vary.
Can you stop GLP-1 after losing weight?
Yes, where clinically appropriate and with the prescribing doctor, and how it is stopped matters. In the STEP 1 extension, where the medication and the lifestyle support stopped on the same day with no taper, about two-thirds of the lost weight returned within a year, and the group still finished 5.6% below its starting weight (Wilding 2022). At GetLean the dose is stepped down at Dr Quek's monthly reviews rather than stopped overnight. Individual results vary.
Has anyone stopped GLP-1 and kept weight off?
In the trials, on average, part of the weight stayed off after the medication ended. The STEP 1 extension group was still 5.6% below its starting weight a year after stopping (Wilding 2022), and in SURMOUNT-4 the group switched to placebo was still 9.9% below its starting weight at week 88 (Aronne 2024). In a Copenhagen randomised trial, adults who had combined the medication with supervised exercise were more likely than those who had taken the medication alone to still hold a loss of at least 10% a year after treatment ended (Jensen 2024). Stepping down is a different picture again: in SURMOUNT-MAINTAIN, adults who stepped down to a lower dose of tirzepatide after 60 weeks were still 16.6% below their starting weight a year later (Horn 2026). These are group averages; individual results vary.